Showing posts with label Outcomes. Show all posts

Monday, October 3, 2022

How are you?


Cartoon of a person answering the question how are you with "about half a standard deviation below the mean"


A simple question, theoretically, has a simple answer. That's not necessarily the case in a clinical trial, though. To measure in a way that can detect differences between groups, researchers often have to use methods that bear no relationship to how we think of a problem, or usually describe it.

Pain is a classic example. We use a lot of vivid words to try to explain our pain. But in a typical health study, that will be standardized. If that were done with what's called a "dichotomous" outcome – a straight up "yes or no" type question – it can be easy to understand the result.

But outcomes like pain can be measured on a scale, which is a "continuous" outcome: how bad is that pain, from nothing to the worst you can imagine? By the time average results between groups of people's scores get compared, it can be hard to translate back into something that makes sense. That's what the woman in the cartoon here is doing: comparing herself to people on a scale.

It pays to never put too much weight on the name of an outcome – check what it really means in the context of that study. There could be fine print that would make a difference to you – for example, “mortality” is measured, but only in the short-term, and you might have to dig hard to figure that our. Or the name the outcome is given might not be what it sounds like at all. People use the same names for outcomes they measure very differently.

Even something that sounds cut and dried can be...complicated. “Perinatal mortality” – death around childbirth – starts and ends at different times before and after birth, from country to country. “Stroke” might mean any kind, or some kinds. And then there's the complexity of composite outcomes – where multiple outcomes are combined and treated as if they're a single one. More on that here at Statistically Funny.

Some researchers put in the hard work of interpreting study measures to make sense in human terms. It would help the rest of us if more of them did that!


This post is based on a section of a post on deciphering outcomes in clinical trials at my Absolutely Maybe blog.

Hilda Bastian

Monday, December 4, 2017

A Science Fortune Cookie


This fortune cookie could start a few scuffles. It's offering a cheerful scenario if you are looking for a benefit of a treatment, for example. But it sure would suck if you are measuring a harm! That's not what's contentious about it, though.

It's the p values and their size that can get things very heated. The p value is the result you get from a standard test for statistical significance. It can't tell you if a hypothesis is true or not, or rule out coincidence. What it can do is measure an actual result against a theoretical expectation, and let you know if this is pretty much what you would expect to see if a hypothesis is true. The smaller it is, the better: statistical significance is high when the p value is low. Statistical hypothesis testing is all a bit Alice-in-Wonderland!

As if it wasn't already complicated enough, people have been dividing rapidly into camps on p values lately. The p value has defenders - we shouldn't dump on the test, just because people misuse it, they say (here). Then there are those who think it should be abandoned or at least very heavily demoted (here and here, for example).

Then there is the camp in favor of raising the bar by lowering the level for p values. In September 2017, a bunch of heavy-hitters say the time has come to expect p values to be much tinier, at least when something new is claimed (here).

How tiny are they saying a p should be? The usual threshold has been p <0.05 (less than 5%). Instead of that being a significant finding, they decided, just a bit less than 0.05 should only be called "suggestive" of a significant finding. A significant new finding should be way tinier: <0.005.

That camp reckons support for this change has reached critical mass. Which is suggestive of the <0.05 threshold going the way of the dodo. I have no idea what the fortune cookie on that says! (If you want to read more on avoiding p value potholes, check out my 5 tips on Absolutely Maybe.)

Now let's get back to the core message of our fortune cookie: the size of a p value is a completely separate issue from the size of the effect. That's because the size of a p value is heavily affected by the size of the study. You can have a highly statistically significant p value for a difference of no real consequence.

There's another trap: an important effect might be real, but the study was too small to know for sure. Here's an example. It's a clinical trial of getting people to watch a video about clinical trials, before going through the standard informed consent process to join a hypothetical clinical trial. The control group went through the same consent process, but without the video.

The researchers looked for possible effects on a particular misconception, and on willingness to sign up for a trial. They concluded this (I added the bold):

An enhanced educational intervention augmenting traditional informed consent led to a meaningful reduction in therapeutic misconception without a statistically significant change in willingness to enroll in hypothetical clinical trials.

You need to look carefully when you see statements like this one. You might not be getting an accurate impression. Later, the researchers report:


[T]his study was powered to detect a difference in therapeutic misconception score but not willingness to participate.


That means they worked out how many people they needed to recruit based only on what was needed to detect a difference of several points in the average misconception scores. Willingness to join a trial dropped by a few percentage points, but the difference wasn't statistically significant. That could mean it doesn't really reduce willingness - or it could mean the study was too small to answer the question. There's just a big question mark: this video reduced misconception, and a reduction in willingness to participate can't be ruled out.

What about the effect size? That is how big (or little) the difference between groups is. There are many different ways to measure it. For example, in this trial, "willingness to participate" was simply the proportion of people who said "yes" or "no".

However, the difference in "misconception" in that trial was measured by comparing mean results people scored on a test of their understanding. You can brush up on means, and how that leads you to standard deviations and standardized mean differences here at Statistically Funny.

There are other specific techniques used to set levels of what effect size matters - but those are for another day. In the meantime, there's a technical article explaining important clinical differences here. And another on Cohen's d, a measure that is often used in psychological studies. It comes with this rule of thumb: 0.2 is a small effect, 0.5 is medium, and 0.8 is a large effect.

Study reports should allow you to come to your own judgment about whether an effect matters or not. May the next research report you read be written by people who make that easy!


Number needed to confuse: read more at Statistically Funny on the objectivity - or not! - in ways of communicating about effects.


Sunday, September 11, 2016

The Highs and Lows of the "Good Study"

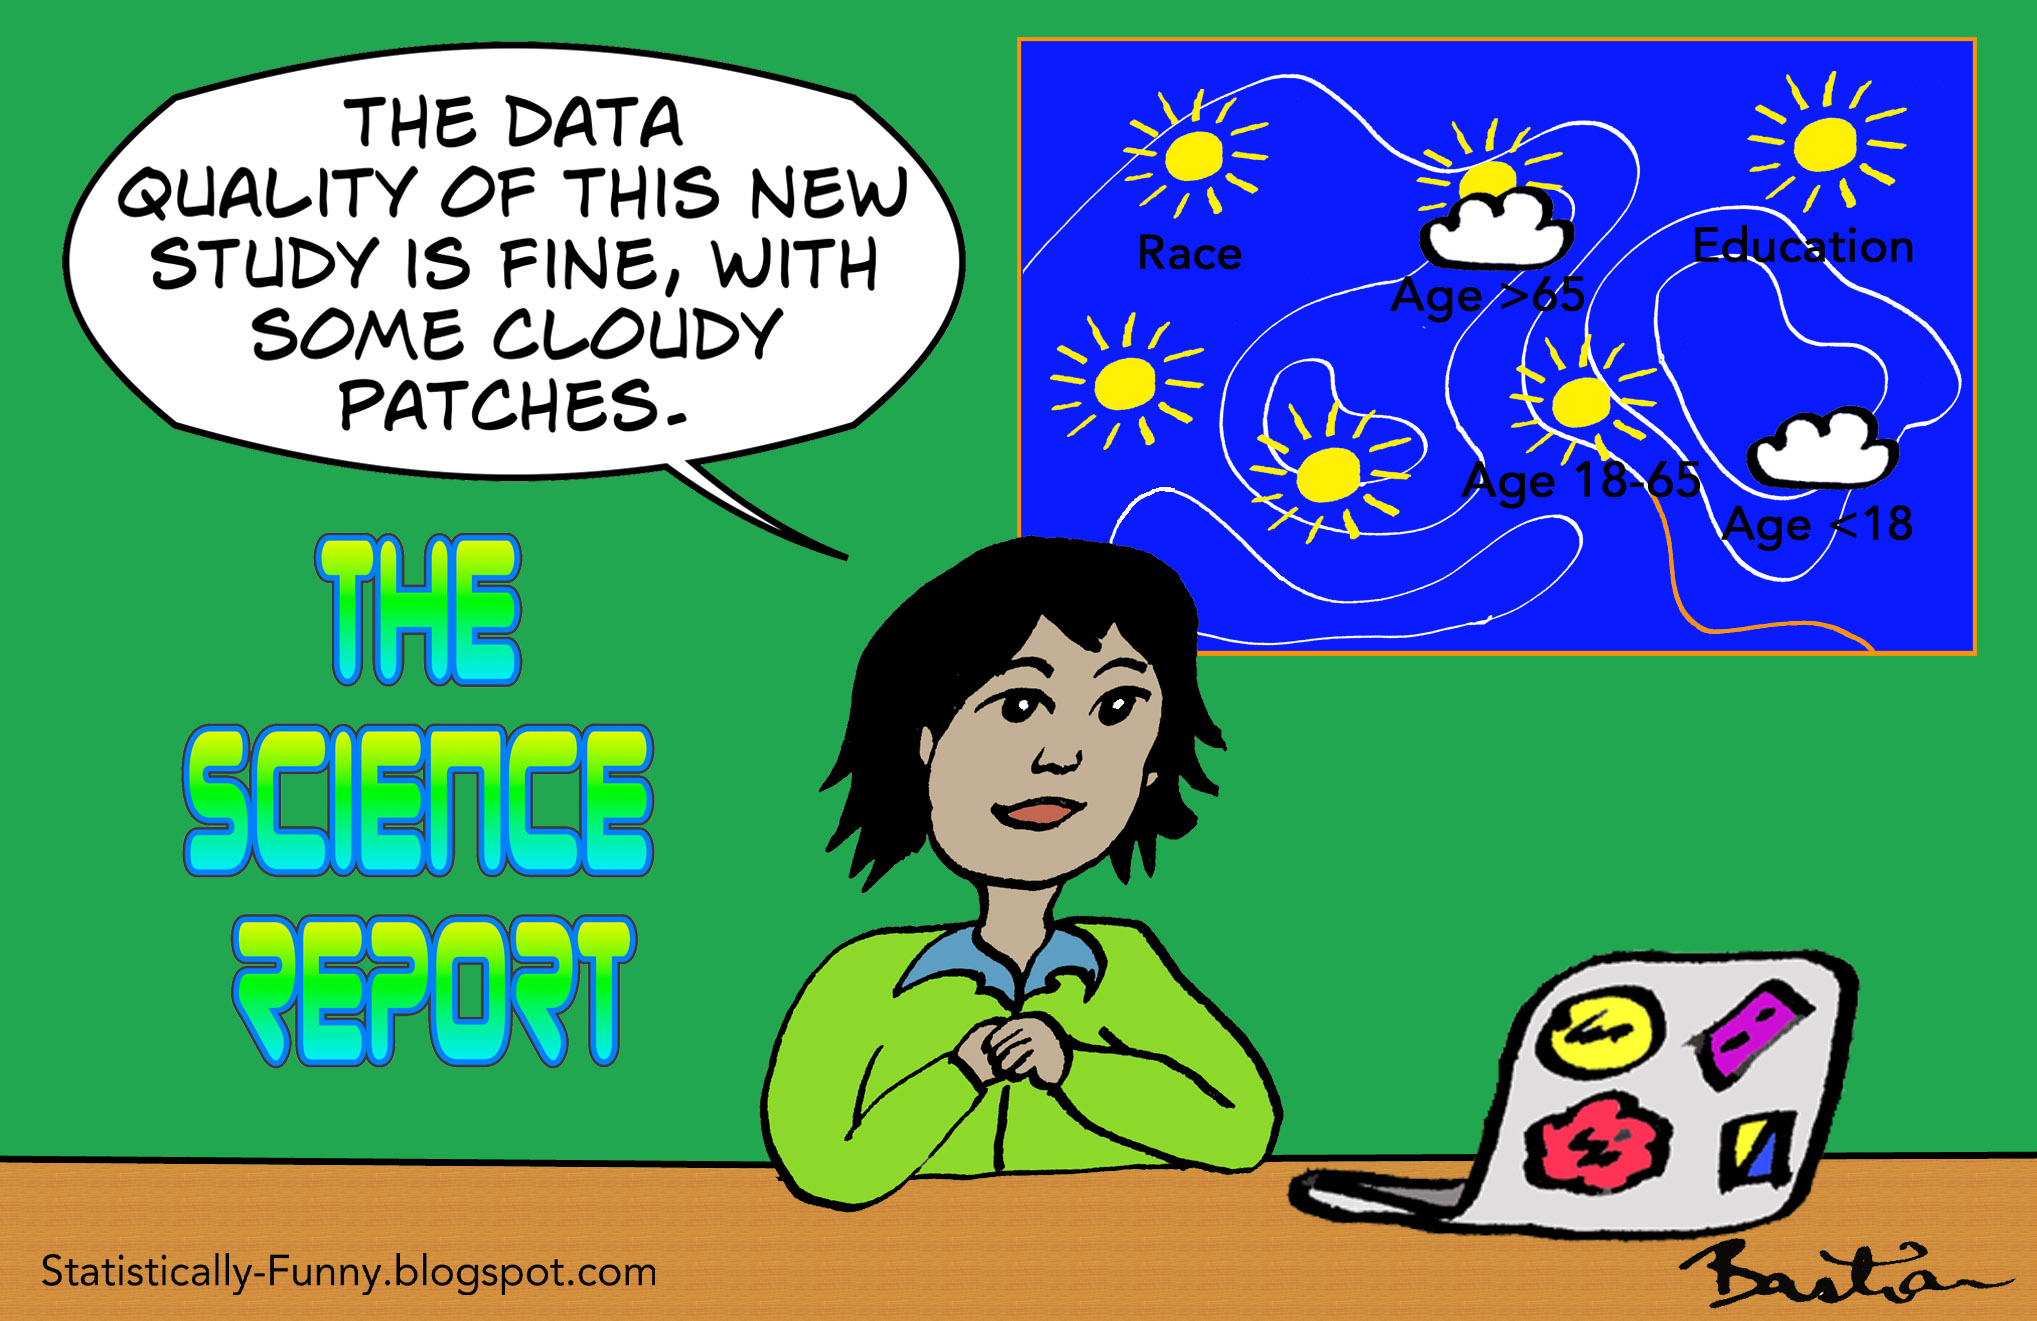
Reporting on a study as though it's a weather report. Scientist at a desk has a map behind them, showing "sunny" for education, but cloudy for data on under-18s. (Cartoon by Hilda Bastian.)


Imagine if weather reports only gave the expected average temperature across a whole country. You wouldn't want to be counting on that information when you were packing for a trip to Alaska or Hawaii, would you?

Yet that's what reports about the strength of scientific results typically do. They will give you some indication of how "good" the whole study is: and leave you with the misleading impression that the "goodness" applies to every result.

Of course, there are some quality criteria that apply to the whole of a study, and affect everything in it. Say I send out a survey to 100 people and only 20 people fill it in. That low response rate affects the study as a whole.

You can't just think about the quality of a study, though. You have to think about the quality of each result within that study. The likelihood is, the reliability of data will vary a lot.

For example, that imaginary survey could find that 25% of people said yes, they ate ice cream every week last month. That's going to be more reliable data than the answer to a question about how many times a week they ate ice cream 10 years ago. And it's likely to be less reliable than their answers to the question, "What year were you born?"

Then there's the question of missing data. Recently I wrote about bias in studies on the careers of women and men in science. A major data set people often analyze is a survey of people awarded PhDs in the United States. Around 90% of people answer it.

But within that, the rate of missing data for marital status can be around 10%, while questions on children can go unanswered 4 times as often. Conclusions based on what proportion of people with PhDs in physics are professors will be more reliable than conclusions on how many people with both PhDs in physics and school-age children are professors.

One of the most misleading areas of all for this are the abstracts and news reports of meta-analyses and systematic reviews. It will often sound really impressive: they'll tell you how many studies, and maybe how many people are in them, too. You could get the impression then, that this means all the results they tell you about have that weight behind them. The standard-setting group behind systematic review reporting says you shouldn't do that: you should make it clear with each result. (Disclosure: I was part of that group).

This is a really big deal. It's unusual for every single study to ask exactly the same questions, and gather exactly the same data, in exactly the same way. And of course that's what you need to be able to pool their answers into a single result. So the results of meta-analyses very often draw on a subset of the studies. It might be a big subset, but it might be tiny.

To show you the problem, I did a search this morning at the New York Times for "meta-analysis". I picked the first example of a journalist reporting on specific results of a meta-analysis of health studies. It's this one: about whether being overweight or obese affects your chances of surviving breast cancer. Here's what the journalist, Roni Caryn Rabin wrote - and it's very typical:

     "Just two years ago, a meta-analysis crunched the numbers from more than 80 studies involving more than 200,000 women with breast cancer, and reported that women who were obese when diagnosed had a 41 percent greater risk of death, while women who were overweight but whose body mass index was under 30 had a 7 percent greater risk".

There really was not much of a chance that all the studies had data on that - even though you would be forgiven for thinking that when you looked at the abstract. And sure enough, this is how it works out when you dig in:

  • There were 82 studies and the authors ran 31 basic meta-analyses;
  • The meta-analytic result with the most studies in it included 24 out of the 82;
  • 84% of those results combined 20 or fewer studies - and 58% had 10 or less. Sometimes only 1 or 2 studies had data on a question;
  • The 2 results the New York Times reported came from about 25% of the studies and less than 20% of the women with breast cancer.

The risk data given in the study's abstract and the New York Times report did not come from "more than 200,000 women with breast cancer". One came from over 42,000 women and the other from over 44,000. In this case, still a lot. Often, it doesn't work that out way, though.

So be very careful when you think, "this is a good study". That's a big trap. It's not just that all studies aren't equally reliable. The strength and quality of evidence almost always varies within a study.


Want to read more about this?

Here's an overview of the GRADE system for grading the strength of evidence about the effects of health care.

I've written more about why it's risky to judge a study by its abstract at Absolutely Maybe.

And here's my quick introduction to meta-analysis.

Sunday, February 8, 2015

Let's Play Outcome Mash-up - A Clinical Trial Shortcut Classic!


Deciphering trial outcomes can be a tricky business. As if many measures aren't hard enough to make sense of on their own, they are often combined in a complex maneuver called a composite endpoint (CEP) or composite outcome. The composite is treated as a single outcome. And journalists often phrase these outcomes in ways that give the impression that each of the separate components has improved.

Here's an example from the New York Times, reporting on the results of a major trial from the last American Heart Association conference:
"There were 6.4% fewer cardiac events - heart disease deaths, heart attacks, strokes, bypass surgeries, stent insertions and hospitalization for severe chest pain..."
That individual statement sounds like the drug reduced deaths, bypasses, stents, and hospitalization for unstable angina, doesn't it? But it didn't. The modest effect was on non-fatal heart attacks and stroke only.*

CEPs are increasingly common: by 2007, well over a third of cardiovascular trials were using them. CEPs are a clinical trial shortcut because you need fewer people and less time to hit a jackpot. A trial's main pile of chips is riding on its pre-specified primary outcome: the one that answers the trial's central, most important question.

The primary outcome determines the size and length of the trial, too. For example, if the most important outcome for a chronic disease treatment is to increase the length of people's lives, you would need a lot of people to get enough events to count (the event in this case would be death). And it would take years to get enough of those events to see if there's anything other than a dramatic, sudden difference.

But if you combine it with one or more other outcomes - like non-fatal heart attacks and strokes - you'll get enough events much more quickly. Put in lots, and you're really hedging your bets.

It's a very valuable statistical technique - but it can go haywire. Say you have 3 very serious outcomes that happen about as often as each other - but then you add another component that is less serious and much more common. The number of less serious events can swamp the others. Everything could even be riding on only one less serious component. But the CEP has a very impressive name - like "serious cardiac events." Appearances can be deceptive.

Enough data on the nature of the events in a CEP should be clearly reported so that this is obvious, but it often isn't. And even if the component events are reported deep in the study's detail, don't be surprised if it's not pointed out in the abstract, press release, and publicity!

There are several different ways a composite can be constructed, including use of techniques like weighting that need to be transparent. Because it's combining events, there has to be a way of dealing with what happens when more than one event happens to one person - and that's not always done the same way. The definitions might make it obvious, the most serious event might count first according to a hierarchy, or the one that happened to a person first might be counted. But exactly what's happening often won't be clear - maybe even most of the time.

There's agreement on some things you should look out for (see for example Montori, Hilden, and Rauch). Are each of the components as serious as each other and/or likely to increase (or decrease) together in much the same way? If one's getting worse and one's getting better, this isn't really measuring one impact.

The biggest worry, though, is when researchers play the slot machine in my cartoon (what we call the pokies, "Downunder"). I've stressed the dangers of hunting over and over for a statistical association (here and here). The analysis by Lim and colleagues found some suggestion that component outcomes are sometimes selected to rig the outcome. If it wasn't the pre-specified primary outcome, and it wasn't specified in the original entry for it in a trials register, that's a worry. Then it wasn't really a tested hypothesis - it's a new hypothesis.

Composite endpoints, properly constructed, reported, and interpreted are essential to getting us decent answers to many questions about treatments. Combining death with serious non-fatal events makes it clear when there's a drop in an outcome largely because people died before that could happen, for example. But you have to be very careful once so much is compacted into one little data blob.


 (Check out slide 14 to see the forest plot of results for the individual components the journalist was reporting on. Forest plots are explained here at Statistically Funny.)


More on understanding clinical trial outcomes:


New this week: I'm delighted to now have a third blog, one for physicians with the wonderful team at MedPage Today. It's called Third Opinion.


Sunday, November 30, 2014

Biomarkers Unlimited: Accept Only OUR Substitutes!


Sounds great, doesn't it? Getting clinical trial results quickly has so much going for it. Information sooner! More affordable trials!

Substituting outcomes that can take years, or even decades, to emerge, with ones you can measure much earlier, makes clinical research much simpler. This kind of substitute outcome is called a surrogate (or intermediate) endpoint or outcome.

Surrogates are often biomarkers - biological signs of disease or a risk factor of disease, like cholesterol in the blood. They are used in clinical care to test for, or keep track of, signs of emerging or progressing disease. Sometimes, like cholesterol, they're the target of treatment.

The problem is, these kinds of substitute measures aren't always reliable. And sometimes we find that out in the hardest possible way.

The risk was recognized as soon as the current methodology of clinical trials was being developed in the 1950s. Austin Bradford Hill, who played a leading role, put it bluntly: if the "rate falls, the pulse is steady, and the blood pressure impeccable, we are still not much better off if unfortunately the patient dies."

That famously happened with some drugs that controlled cardiac arrhythmia - irregular heartbeat that increases the chances of having a heart attack. On the basis of ECG tests that showed the heartbeat was regular, these drugs were prescribed for years before a trial showed that they were causing tens of thousands of premature deaths, not preventing them. That kind of problem has happened too often for comfort.

It happened again this week - although at least before the drug was ever approved. A drug company canceled all its trials for advanced gastric (stomach) cancer of a new drug. The drug is called Rilotumumab. Back in January, it was a "promising" treatment, billed as bringing "new hope in gastric cancer." It got through the early testing phases and was in Phase III trials - the kind needed to get FDA approval.

But one phase III trial, RILOMET-1, quickly showed an increase in the number of deaths in people using the drug. We don't know how many yet - but it was enough for the company to decide to end all trials of the substance.

This drug targets a biomarker associated with worse disease outcomes, an area seen by some as transforming gastric cancer research and treatment. Others see considerable challenges, though - and what happened to the participants in the RILOMET-1 trial underscores why.

There is a lot of controversy about surrogate outcomes - and debates about what's needed to show that an outcome or measure is a valid surrogate we can rely on. They can lead us to think that a treatment is more effective than it really is.

Yet a recent investigative report found that cancer drugs are being increasingly approved based only on surrogate outcomes, like "progression-free survival." That measures biomarker activity rather than overall survival (when people died).

It can be hard to recognize at first, what's a surrogate and what's an actual health outcome. One rule of thumb is, if you need a laboratory test of some kind, it's more likely to be a surrogate. Whereas symptoms of the disease you're concerned, or harm caused by the disease, are the direct outcomes of interest. Sometimes those are specified as"patient-relevant outcomes."

Many surrogate outcomes are incredibly important, of course - viral load for HIV treatment and trials for example. But in general, when clinical research results are based only on surrogates, the evidence just isn't as strong and reliable as it is for the outcomes we are really concerned about.

~~~~

See also, Statistically Funny on "promising" treatments.

Sunday, July 28, 2013

Alleged effects include howling


When dogs howl at night, it's not the full moon that sets them off. Dogs are communicating for all sorts of reasons. We're just not all that good at understanding what they're saying.

We make so many mistakes about attributing cause and effect for so many reasons, that it's almost surprising we get it right as often as we do. But all those mistaken beliefs we realize we have, don't seem to teach us a lesson. Pretty soon after catching ourselves out, we're at it again, taking mental shortcuts, being cognitive misers.

It's so pervasive, you would think we would know this about ourselves, at least, even if we don't understand dogs. Yet we commonly under-estimate how much bias is affecting our beliefs. That's been dubbed the bias blind spot that we tend to live in.

Even taking all that into account, "effect" is an astonishingly over-used word, especially in research and science communication where you would hope people would be more careful. The maxim that correlation (happening at the same time) does not necessarily mean causation has spread far and wide, becoming something of a cliche along the way.

But does that mean that people are as careful with the use of the word "effect" as they are with the use of the "cause" word? Unfortunately not.

Take this common one: "Side effects include...." Well, actually, don't be so fast to swallow that one. Sometimes, genuine adverse effects will follow that phrase. But more often, the catalogue that follows is not adverse effects, but a list of adverse events - things that happened (or were reported). Some of them may be causally related, some might not be.

You have to look carefully at claims of benefits and harms. Even researchers who aren't particularly biased will word it carelessly. You will often hear that 14% experienced nausea, say - without it being pointed out that 13% of people on placebos also experienced nausea, and the difference wasn't statistically significant. Some adverse effects are well known, and it doesn't matter (diarrhea and antibiotics, say). That's not always so, though. (More on this: 5 Key Things to Know About Adverse Effects.)

If the word "effect" is over-used, the word "hypothesis" is under-used. Although generating hypotheses is a critical part of science, hypotheses aren't really marketed as what they are: ideas in need of testing. Often the language is that of attribution throughout, with a little fig-leaf of a sentence tacked on about the need for confirmatory studies. In fact, we cannot take replication and confirmation for granted at all.